


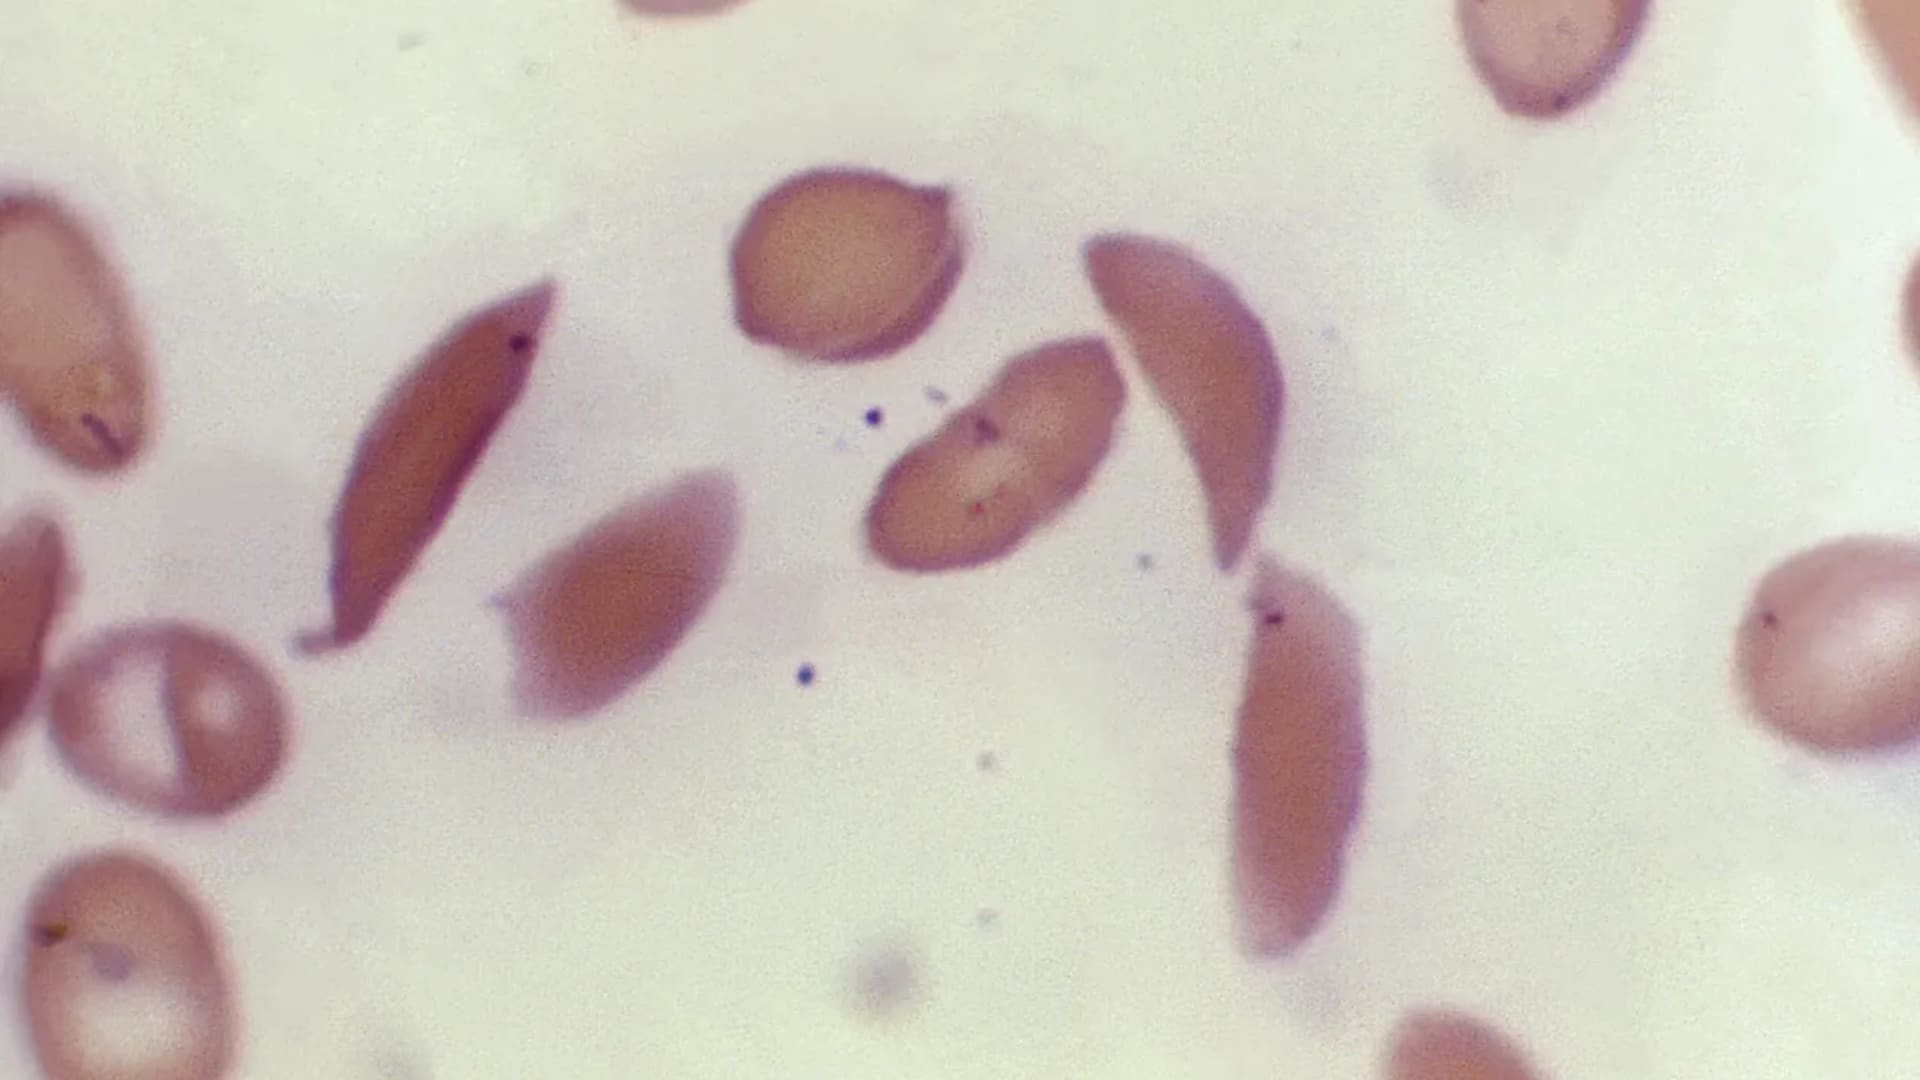
A microscope image released on October 25, 2023, by the Centers for Disease Control and Prevention displays crescent-shaped red blood cells from a patient with sickle cell disease, dating back to 1972. Recently, the UK’s medicine regulatory agency has approved the first gene therapy intended for sickle cell disease, potentially offering hope to many suffering from this debilitating condition in the U.K.
For many years, those affected by sickle cell disease have dealt with frequent hospital visits, medication regimens, and blood transfusions to manage a painful genetic blood condition that can reduce life expectancy by up to 20 years.
However, 2023 marked a significant turning point, as the U.S. Food and Drug Administration gave the green light to Casgevy and Lyfgenia, the pioneering gene therapies designed for severe cases of sickle cell disease. Advocates and medical professionals believe that these advancements might signal the dawn of a new age in managing sickle cell disease, offering relief from recurrent pain episodes and promising improved health outcomes.
“This opens up a whole world where individuals could potentially be cured of sickle cell disease,” stated Dr. Edward Donnell Ivy, the chief medical officer at the Sickle Cell Disease Association of America.
Nevertheless, for many living with the disease, obtaining these groundbreaking therapies is still quite challenging.
Patients often navigate a fragmented healthcare system where the availability of treatment options, costs, and access to specialized centers can significantly differ based on their location. As a result, many who could benefit from these therapies find them inaccessible.
“Understanding the patients’ priorities is essential for figuring out the barriers to access and how to overcome them,” explained Dr. Alexis Thompson, a hematology chief at Children’s Hospital of Philadelphia and spokesperson for the American Society of Hematology.
Path to a breakthrough
Often called “the most common rare disease,” sickle cell disease affects around 100,000 individuals in the U.S., predominantly among the non-Hispanic Black or African American population.
This genetic blood disorder alters normally flexible red blood cells into rigid, crescent shapes, which can obstruct blood flow and hinder oxygen delivery to tissues.
Common complications include chronic fatigue, anemia, blood clots, and painful crises that can result in severe pain lasting from a few hours to weeks. Other potential complications range from strokes to organ damage, heightening the risk of infections.
…from 1910 until about 2015, there was very little progress in disease-modifying treatments for sickle cell disease.”
Dr. Andrew Campbell
Children’s National Director of Sickle Cell Disease Program
More than a century ago, in 1910, the first documented case of sickle cell disease appeared in the U.S., and since then, advancements in treatment have been slow, partly due to significant underfunding and less philanthropic support compared to other genetic disorders. Between 2008 and 2018, funding per patient from the National Institutes of Health for sickle cell disease averaged $812, whereas it was $2,807 for cystic fibrosis, which affects about 40,000 in the U.S.
“Therapeutic advancements were slow until recently,” noted Dr. Andrew Campbell, director of the Children’s National sickle cell program. “In the last six to seven years, however, there’s been a significant upsurge in new therapies. From 1910 to about 2015, progress in disease-modifying treatments was minimal.”
A notable advancement came in 1998 with the FDA’s approval of hydroxyurea, the first drug recognized to modify the effects of sickle cell disease. Research indicates that hydroxyurea can decrease the frequency of painful crises by approximately half and lower the need for hospital visits and blood transfusions, making it a foundational treatment that has benefited countless patients.
Despite these developments, a definitive curative option was hard to find until the introduction of gene therapy. Previously, bone marrow transplants were the primary treatment available, but it was restrictive due to the difficulty in finding suitable donors.
“Though bone marrow transplants existed, they had limited accessibility because finding a donor was tough,” Ivy commented, noting that now individuals can potentially be their own donors thanks to cell and gene therapies.
Slow patient uptake
Gene therapy has exhibited impressive efficacy, with 88% to 94% of patients experiencing complete relief from severe pain crises.
However, the adoption of gene therapies for sickle cell disease has been gradual. By the end of 2025, 64 patients worldwide had received Casgevy infusions, accompanied by another 147 starting their treatment process. Lyfgenia’s developer, Genetix Biotherapeutics, reported that 115 U.S. patients were treated with this gene therapy since its approval in 2023, with an extra 216 beginning their treatment preparations by late 2025.
The gene therapy process can be quite intimidating, possibly discouraging some patients. It involves the extraction of blood-forming stem cells which are modified to create healthy hemoglobin before being reinstated into the body. There’s also a conditioning phase that involves chemotherapy and frequent hospital stays, which can last for several weeks.
This entire treatment can extend up to a year, and the conditioning may lead to permanent infertility or sterility.
Currently, Casgevy is approved for patients as young as two, while Lyfgenia is available for those aged twelve and over, both targeting severe disease cases such as HbSS and HbS beta “zero” thalassemia. Candidates usually include patients who have faced at least four pain crises or acute chest syndrome episodes within a two-year span before seeking treatment. Some studies estimate that 25% to 35% of patients meet the eligibility criteria for gene therapy.
Ivy recalls enduring multiple painful crises annually that necessitated hospitalization until he began hydroxyurea as part of a study. He noted how it significantly improved his life, helping him finish his medical education without major interruptions.
However, he ultimately decided against pursuing gene therapy due to the physical and time-related demands involved. “Had I been younger, I surely would’ve considered it,” he admitted, “But there are many factors to weigh.”
On top of the physical strain, the financial aspect of gene therapy could deter many patients from pursuing it. The cost for a single treatment can range between $2.2 million and $3.1 million, not accounting for related healthcare costs like hospital stays and necessary specialized care.
There have been initiatives aimed at mitigating the cost disparities between those with private insurance and the majority who rely on Medicaid or the Children’s Health Insurance Program. Dr. Alexis Thompson mentioned a significant effort initiated in 2024 by the Centers for Medicare and Medicaid Services. The Cell and Gene Therapy Access Model aims to negotiate pricing based on patient outcomes to ease the financial burden of therapy and care, with participation from 32 states, D.C., and Puerto Rico.
However, Thompson pointed out that the range of services covered can vary by state, leading to inconsistencies in accessibility. Despite Medicaid covering gene therapy costs for sickle cell disease, the bigger issue may be the complex financial landscape that healthcare providers must navigate as they deal with significant upfront expenses before reimbursement is settled.
Finding a qualified healthcare provider willing to offer gene therapy may pose a larger obstacle than costs, as hospitals need a team of experts to adequately support patients pre-treatment, during, and post-treatment.
…there is a mismatch between the number of patients and the number of providers – that means some patients are driving from up to three hours away to gain access to sickle cell expertise.”
Dr. Christina Abrams
Director of the Pediatric Sickle Center at the Medical University of South Carolina’s Shawn Jenkins Children’s Hospital in Charleston
While various major academic health institutions across the nation provide gene therapy, the limited number of specialized care centers often leaves a gap in care for individuals in more remote areas, requiring long journeys for treatment. Dr. Christina Abrams, who oversees the Pediatric Sickle Center at the Medical University of South Carolina, noted that in South Carolina, several patients are commuting for hours to receive care due to an inadequacy in specialists.
“In our state, we only have three main centers serving sickle cell disease patients,” Abrams explained. “And often, there’s this disparity between the number of patients and the number of providers, meaning some patients are driving quite far just to access specialized care.”
Bridging the gap
To address these accessibility challenges, Abrams mentioned her center is implementing ongoing support services that include social workers, patient navigators, and virtual consultation options.
Similar initiatives to improve access are underway at UAB, where a project called Recruitment and Engagement in Care to Impact Practice Enhancement for Sickle Cell Disease, or RECIPE, was launched in 2021. The aim is to identify and recruit sickle cell patients who might not have seen a specialist into proper care.
One goal is to reach patients aged 35 and older, who may not have received a diagnosis at birth, and connect them with specialists.
“Our focus is really helping those in areas unaware of their need for care,” said Kanter.
On a broader scale, efforts are being made to establish a stronger national sickle cell disease care network through the National Alliance of Sickle Cell Centers, which includes sickle cell centers at both UAB and MUSC. With 115 member centers nationwide, Abrams mentioned that the Alliance is working towards improving collaboration among specialists and increasing awareness among the medical community to deepen the understanding of the disease.
“Sickle cell disease lacks standard care and recognition, which has been a long-standing issue,” Abrams pointed out. “Being part of this organization enhances our participation in broader initiatives.”
CNBC Cures is backed by Alexion, AstraZeneca Rare Disease, and BridgeBio.





