


Colorectal Cancer Surges in Nigeria Amid Late Diagnoses
A small business owner discovered he had appendicitis. A government clerk and a university lecturer, both suffering from stomach issues for over a year, were initially misdiagnosed with ulcers. Unfortunately, each had colorectal cancer, and by the time they found out, they required significant surgery and nearly a year of draining chemotherapy treatments.
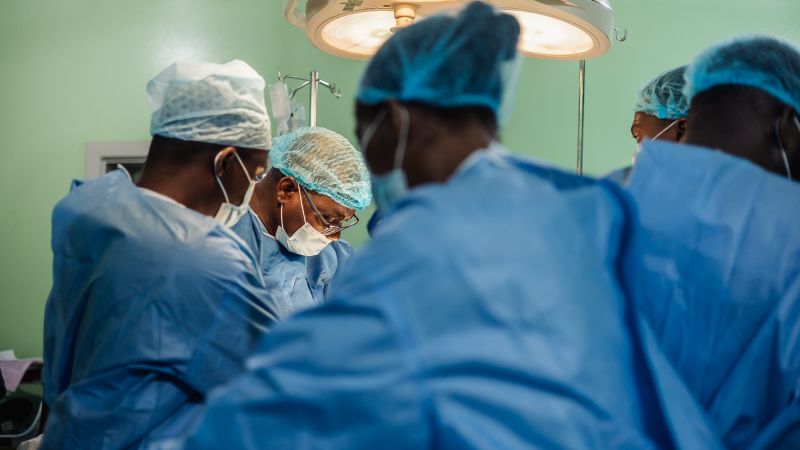
These individuals shared their experiences with CNN while living in and around Ile-Ife, a city in southwestern Nigeria. Eventually, all three were treated at the Obafemi Awolowo University Teaching Hospital, where Dr. Olusegun Alatise, a surgical professor, operated.
When Alatise started his surgical training in the early 2000s, he was told colorectal cancer was rare in sub-Saharan Africa. Yet, this didn’t align with what he observed during his practice.
“It was supposed to be very rare, but we [the hospital] were seeing a case every week,” he noted, emphasizing the significant rise in colorectal cancer cases.
The situation in Nigeria is dramatically different from that in the US or western Europe. There, about two out of three patients survive five years post-diagnosis, while in Nigeria, it’s only one in five. According to Alatise, a main factor is that Nigerian patients often seek treatment quite late.
“Most come to the hospital only when the disease has progressed,” he explained. “They might experience symptoms like rectal bleeding for an entire year—yet everyone around them is treating them with other remedies.”
Despite the aging facilities and worn-out exam rooms at the OAU hospital, Alatise has formed partnerships that are transforming care not just in Nigeria but across the globe.
His journey began in 2009 when he joined a program aimed at training international doctors to enhance cancer care in their home countries. Hosted at Memorial Sloan Kettering Cancer Center in New York City, Alatise was notably the first African surgeon to enroll.
During his time in New York, he learned innovative surgical techniques and struck up a friendship with Dr. Peter Kingham, an American surgeon seasoned in various African nations. After returning to Nigeria in 2011, Alatise invited Kingham back for several weeks, which soon became an annual tradition. By that time, Kingham had started the Global Cancer Disparities Initiative at Memorial Sloan Kettering. In 2013, the two founded the African Research Group for Oncology (ARGO) to enhance training programs and expand African research opportunities.
“The aim is to generate clinically meaningful research,” Kingham said, pointing out that while elaborate studies may be a luxury elsewhere, in Nigeria, it’s crucial to consider whether research can genuinely impact patients.
Currently, ARGO encompasses over two dozen sites in Nigeria, employing more than 60 staff members and involving nearly 10,000 patients in various research initiatives. At least four grants from the US National Institutes of Health support ARGO’s work, with a strong focus on colorectal cancer.
Colorectal cancer is currently the second leading cause of cancer deaths globally, and cases among young adults are on the rise. Although colorectal cancer rates are typically lower in Africa and South Asia compared to the US and Europe, the gap is narrowing.
Factors such as genetics, smoking, and alcohol consumption contribute to the risk, but Kingham attributes the rise mainly to changing diets. “Western diets, along with processed foods, are strongly associated with colorectal cancer,” he remarked, noting that this trend seems to accompany development.
Alatise believes the Nigerian diet has changed greatly over the years. “Even those from rural areas are primarily consuming processed foods now, as they’re seen as a status symbol,” he explained. “Meanwhile, high-fiber traditional diets are often viewed as food for those who can’t afford better.” It’s curious, really—while affluent people overseas seek to incorporate more fiber, in Africa, many are striving for a more Western lifestyle.
Recognizing the challenges in changing dietary habits, Alatise saw improving screening as a quicker solution for better patient outcomes. In 2014, ARGO launched pilot projects to identify cases earlier. In the first study, 362 patients with rectal bleeding were offered free colonoscopies, revealing that nearly 20% were diagnosed with colorectal cancer—crucially, 74% of these cases were detected at a potentially curable stage. Interestingly, the study also found that rectal bleeding alone doesn’t always indicate cancer, but when paired with weight loss and changes in bowel habits, it becomes a significant warning sign.
This insight is critical for optimizing the limited resources in Nigeria, where the cost of a colonoscopy is about half the average monthly income. ARGO’s studies also highlighted that cheaper screening tests, which detect blood in stools, are impractical for large-scale implementation due to the expensive follow-up colonoscopies needed for positive results.
More recently, Alatise and his team took on the problem of missed symptoms and late diagnoses. They initially used radio jingles and flyers to raise awareness about the need for early detection. They also trained healthcare providers at local clinics to identify specific symptoms better.
The messages were straightforward. Providers learned to look for symptom combinations, particularly bleeding and weight loss, which had proven significant in the earlier study. “They received guidance on recognizing these symptoms, determining patient history, and when to refer them for screening,” explained Dr. Tajudeen Mohammed, a surgeon involved in the initiative.
Engaging patients was tricky, though. The individuals CNN spoke with revealed that their previous doctors often treated the subject of cancer as taboo. Some said they learned of their diagnoses not from their physicians but from family. Mayowa Ajayi, a government clerk, admitted he hadn’t even heard of colorectal cancer until he ended up in the hospital. Another university lecturer, given anti-ulcer treatments for months while suffering severe pain, preferred to remain anonymous, fearing health complications would affect her relationships with colleagues.
Chris Bamidele, a research associate supervising ARGO’s colorectal cancer studies, noted that many patients fear seeking help, while others hold religious beliefs that cloud perceptions of cancer. Moreover, transportation issues and an inability to afford medical visits often lead them to rely on herbal remedies instead.
Despite these obstacles, the healthcare workers involved in the pilot program felt encouraged by the results. Over 300 individuals were referred for free colonoscopies through the project, uncovering four early-stage cancer diagnoses and 13 high-risk precancerous polyps that were easily addressed. Alatise shared that even two of his senior colleagues, curious about the screenings, could have faced severe risks had they not participated. “We removed the polyps, saved their lives, and now they’re doing remarkably well,” he added.
Nevertheless, there are significant challenges to wider implementation. Alatise pointed out that the research group continues to enhance healthcare provider education while collaborating with Memorial Sloan Kettering and the University of Alberta to develop a urine-based screening test for colorectal cancer.
The team’s research is not confined to screening alone. Recently, they initiated a trial using tislelizumab, an immune checkpoint inhibitor, aimed at helping the body fight cancer cells. This is among the few immunotherapy trials conducted in sub-Saharan Africa. Kingham emphasized that tislelizumab appears to be particularly effective in patients with a specific genetic profile that’s three times more common in Nigeria than in the US. “This means it could offer significant benefits to patients here,” he mentioned.
By working to improve cancer care in Nigeria, Kingham believes they also have a unique opportunity to advance patient care globally. Clinical trial procedures, while often costly for Nigerians, can be offered at a fraction of the expense compared to higher-income nations, maximizing the impact of research funding.
But those considerations felt like background noise as a university lecturer shared her health journey over the past five years. She defied the odds following a late diagnosis and, now cancer-free, urges others to not wait as long as she did. “Getting screened can be uncomfortable, but the discomfort is insignificant compared to the reality of dealing with cancer,” she advised. “I encourage everyone to go for it.”





