Study design and participants
This retrospective case-control study was conducted according to institutional guidelines and received approval from the Institutional Review Board of Memorial Sloan Kettering Cancer Center (MSK), under protocol number 17-581. Informed consent was not required as the study involved secondary analysis of previously collected PET-CT imaging and clinical data, which posed minimal risk to participants and could not be feasibly conducted with individual consent. Data for all patients were anonymized prior to analysis.
Previously, we created a cohort of patients with brown adipose tissue (BAT) by examining 18F-FDG-PET–CT scans done at MSK between June 2009 and March 2018. Patients with BAT detected in at least one scan were classified as BAT+, while others were labeled BAT−. To broaden this group, we established a new Extension BAT Cohort by similarly reviewing all 18F-FDG-PET–CT scans at MSK for patients 18 years and older, from April 2018 to July 2024. Those showing BAT in any scan were again classified as BAT+, and the rest as BAT−. Each patient was assigned an index scan: for those with BAT, it was the earliest scan reporting BAT; for those without BAT, it was their first scan. We gathered demographic information, BMI, outdoor temperature data, and relevant ICD-9 and ICD-10 codes related to cardiometabolic diseases, one year following the index scan, from the institutional EHR. Average outdoor temperatures in New York City were sourced from the US National Weather Service. An initial logistic regression analyzed patients from the Extension BAT Cohort to identify links between BAT presence and cardiometabolic diseases. After confirming an association between BAT presence and reduced prevalence of these diseases in this cohort, we merged it with the Established BAT Cohort to form an Expanded BAT Cohort. If a patient appeared in both cohorts, data from the Established BAT Cohort were prioritized.
Data collection and PSM
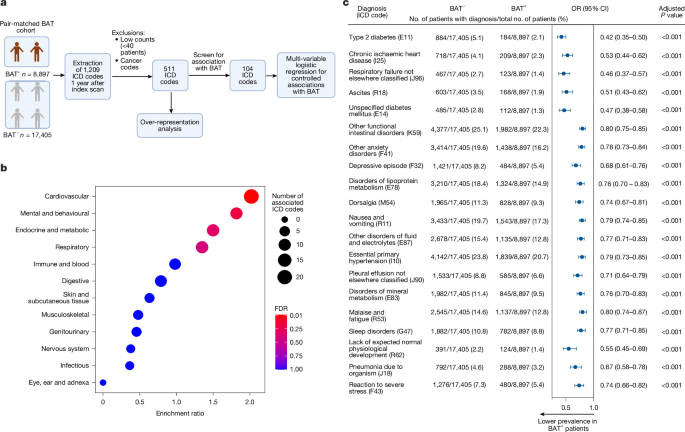
To develop a balanced study cohort from the Expanded BAT Cohort, patients in BAT+ and BAT− groups were matched using propensity score matching (PSM). We estimated the propensity scores with a non-parsimonious multi-variable logistic regression model, using BAT status (presence or absence) as the dependent variable while controlling for age, sex, BMI, and scan temperature. Matching occurred via a greedy nearest neighbor algorithm without replacement, utilizing a calliper width of 0.2 and a matching ratio of 1:2. This process culminated in a final study group encompassing 26,302 patients (8,897 BAT+ and 17,405 BAT−). We conducted balance diagnostics to evaluate the matching success by using standardized mean differences for all variables involved in the propensity score model before and after matching. A post-matching standardized mean difference within the -0.10 to 0.10 range indicated sufficient balance across all measured co-variates between BAT+ and BAT− groups, supporting our causal inference validity based on the PSM design.
We collected relevant clinical data for each patient as outlined before. Briefly, cancer site information included the specific cancer diagnosis code (ICD-0) noted closest to the index scan date. Data on cancer treatment were gathered if administered within 90 days before the index scan and classified in line with previous methods. Relevant ICD-9 and ICD-10 codes linked to cardiometabolic diseases and all other codes were extracted for up to one year post-index scan in the PSM cohort. We selected codes that reflected non-pediatric, non-obstetric, adult disorders.
Regarding laboratory values, clinical indices, and imaging studies, we retrieved available data for up to a year after the index scan from the PSM cohort. Analyses were performed on both BAT+ and BAT− patients with values on record. To identify pharmacological agents associated with BAT presence, we sifted through home medication lists and/or active prescriptions in the EHR for each patient in our cohort. We only included medications documented up to one month before the index scan, excluding those with implausible systemic effects, such as those applied topically or that are typically prescribed for short durations. Additionally, we disregarded medications labeled as ‘as needed’ and herbal supplements, along with low-frequency medications (those present in fewer than 40 patients). A comprehensive list of medications analyzed can be found in supplementary material, categorized as previously indicated.
Selection of diagnostic codes for unbiased associations with BAT
To investigate unbiased correlations between BAT and various diseases, we extracted diagnostic codes (ICD-9 and ICD-10) from the EHR, applicable for up to one year following the index scan, from patients in the PSM cohort. For code selection, we organized ICD-9 and ICD-10 codes based on their initial three characters. ICD-10 codes under general groupings (A-R) were included as they correspond typically to medical issues found within a non-pediatric, non-obstetric, adult cancer demographic. A similar approach was adopted for ICD-9 codes, resulting in 1,157 ICD-10 codes and 626 ICD-9 codes targeted for extraction.
Post extraction, we merged redundant ICD-9 codes with their respective ICD-10 counterparts after a manual review. We maintained the nomenclature of the ICD-10 code for future analyses wherever codes were combined. ICD-9 codes without a matching ICD-10 remained as documented. This process resulted in 1,209 total codes across both individual and merged ICD-9 and ICD-10 codes.
To refine our selection of diagnostic codes for analysis, we excluded codes that appeared with low frequency (less than 40 patients) and those associated with cancer diagnosis due to all patients already having a designated cancer site. This left us with 511 final diagnostic codes. Due to the considerable number of codes, we initially conducted a screening analysis via univariable logistic regression to identify associations of these 511 codes with BAT presence. From this analysis, 104 codes displayed significant associations with BAT status. Following this, we analyzed each of these codes through a multi-variable regression analysis to evaluate their independent association with BAT while accounting for various demographics and clinical factors.
Machine learning approach to quantify BAT activity
The 3DF workflow utilized PET and CT images in DICOM format. Based on the DICOM header data regarding image orientation and patient positioning, PET images were resized to match CT image dimensions via linear interpolation. The images were then converted into .nrrd file format and processed through nnU-net. This model produced mask predictions indicating different anatomical sites, such as cervical or mediastinal regions. After interpretation of the mask predictions by 3DF and subsequent contour generation, these contours were resized to align with the original PET dimensions. Metrics from the original PET images for each site were compiled into an Excel master file. This entire process was executed in batch mode, facilitating the simultaneous segmentation of a large patient cohort. We implemented this technique to assess BAT metabolic activity within 8,709 patients classified as BAT+. A small number of patients (188) in the BAT+ group could not be processed due to discrepancies in field of view between the CT and PET images.
Machine learning approach to quantify SAT and VAT area
The 3DF abdominal adipose tissue workflow was carried out on axial CT images at the L3–L4 intervertebral disc level. Selection of the target slice was automated through TotalSegmentator vertebral segmentation. The body contour on the chosen slice was determined by identifying voxels above -500 Hounsfield units and subsequently refining the shape. Abdominal circumference was calculated using DICOM pixel spacing. Fat voxels within that contour were recognized using specific Hounsfield unit ranges, allowing us to categorize them into subcutaneous and visceral adipose tissue. Measurements such as outer abdominal circumference in centimeters, SAT area, VAT area, and the subcutaneous-to-visceral ratio were consolidated into an Excel master file. This methodology enabled us to analyze white adipose tissue distribution parameters for 8,040 patients with BAT.
Selection of medications for testing in animal and mouse models
Our multi-variable logistic regression analysis indicated that 39 out of 125 medications showed significant correlations with BAT presence. Of the 38 examined, 29 suggested a potential for activating BAT. To find suitable candidates for further testing, we researched each medication emphasizing (1) its impact on adipocyte receptors or pathways, (2) effects directly on adipocytes, and (3) any cardiovascular advantages beyond their primary pharmacological use. Among the 29 medications, losartan and valsartan met these extensive criteria.
Cellular studies in adipocytes
Brown adipocytes, both immortalized and primary types, were cultured and differentiated as previously noted, with procedures conducted on mature adipocytes between days 7 and 10 after differentiation. Cultured cell lines tested negative for mycoplasma. Mature brown adipocytes were subjected to losartan potassium treatment for 24 to 72 hours prior to experiments, with specific dosages also explored. Norepinephrine was applied to stimulate Ucp1 transcription. Additional experiments focused on losartan metabolites and PPARγ inhibition, with corresponding methodologies executed for RNA and protein analyses. Respirometry measurements on mature adipocytes were conducted using 96-well plates as manufacturer-directed.
To simulate beige and white adipocyte behavior, we isolated the stromal vascular fraction from different regions of young mice to enrich for the respective progenitor cell types. This confirmation was evidenced by Ucp1 expression, followed by treatment with losartan and norepinephrine as applied in brown adipocyte experiments.
shRNA-mediated knockdown in brown adipocytes
shRNA sequences targeting At1r were sourced from the Broad Institute’s platform. Oligonucleotides were cloned within a particular vector, and the generated lentivirus was used for brown adipocyte transduction. Following transduction, we initiated puromycin selection at day 4, and these cells were utilized for experiments involving losartan after achieving full differentiation.
PPARγ luciferase reporter assay
HEK293T cells were transfected with several plasmids, including those for PPARγ2 and RXRa, to assess luciferase activity after treatment with varying concentrations of losartan and other compounds. Following overnight transfection, cells were lysed and processed for luciferase assays according to established protocols.
Animal studies and metabolic phenotyping
The study utilized male C57BL/6J mice, maintained under controlled light conditions and with free access to food and water. All aspects of animal care and experimental procedures adhered to guidelines approved by the relevant Institutional Animal Care and Use Committees.
Mice underwent treatment with losartan through oral gavage or drinking water while carefully monitoring intake to maintain dosage. Randomized treatments ensured unbiased results. After the treatment periods, mice were euthanized, and BAT collected for further analyses.
To assess BAT-specific heat production, we performed infrared thermography on treated mice. Acclimatized to specific conditions, mice underwent procedures for thermal imaging that allowed us to analyze the temperature differences indicative of BAT activity, employing established methods for data collection.
Whole-body metabolic measurements were conducted with an advanced metabolic screening system, with individual housing to precisely evaluate energy expenditure under different conditions. These measurements were detailed across light and dark cycles, with variables carefully recorded for analysis.
Energy expenditure was estimated from indirect calorimetry, employing the Weir equation, with activity monitored through sophisticated sensor systems in place. Throughout the study, mice were closely observed to ensure well-being, while data were processed and analyzed through various software.
RNA isolation, cDNA synthesis and real-time PCR
RNA extraction from cultured mature adipocytes was performed using specific buffers and kits. Subsequent cDNA was synthesized through specialized kits, analyzed via real-time PCR using designated primers. Relative mRNA levels were quantified utilizing cycle threshold methods.
Protein extraction and western blot
For protein extraction, cells or tissue were lysed with a comprehensive buffer mix. Extracts were separated via polyacrylamide gels, followed by transfer to membranes for antibody probing. Protein detection involved enhanced techniques, with density quantification executed through imaging analysis software.
Statistical analysis
We utilized Pearson’s correlation to assess the relationship between BAT and various variables. The presence of BAT across genders was analyzed using chi-squared tests.
A multi-variable logistic regression approach was employed to evaluate whether BAT status predicted cardiometabolic diseases, adjusting for numerous co-variates. Activity levels of BAT were calculated and analyzed against disease presence using similar regression techniques, focusing on correlation with clinical variables.
Crude associations of BAT with individual diagnostic codes were identified and followed by more thorough analyses for significant codes. We accounted for potential overlaps and carried out statistical significance assessments through specific adjustments.
Laboratory values and clinical data were compared between BAT+ and BAT− groups using two-sample t-tests, ensuring methodological soundness and proper adjustments were made for variance. Detailed analyses involved several iterations of multi-variable modeling.
Medication influence on BAT was analyzed through logistic regression with appropriate adjustments, while in vitro and in vivo results followed up with stringent statistical tests and corrections for multiple comparisons. All operations were executed utilizing dedicated software tools to maintain rigorous standards.
Reporting summary
Further information regarding research design can be accessed in the additional materials linked to this article.