


New Canadian Method for Atrial Fibrillation Treatment
A recent Canadian method for addressing the common heart rhythm disorder known as atrial fibrillation (AFib) has the potential to significantly improve the lives of affected patients.
AFib is recognized as the most prevalent arrhythmia, occurring in the heart’s upper chambers. It impacts about one to two percent of the overall population, leading to symptoms like shortness of breath and fatigue. Unfortunately, it can also result in serious health complications, including stroke or heart failure.
Jon Davies from Edmonton started to feel a sense of fatigue that led him to think something might be wrong. “I used to enjoy mountain hiking and played squash often, but that changed pretty quickly as I entered my 50s,” he shared during an interview. “I thought it was just getting older, you know, having a desk job and perhaps not exercising enough.”
His wife, Nora, noted he frequently seemed exhausted and would sleep deeply. Eventually, he was diagnosed with AFib, but the treatment options left him taken aback.
“They said my heart had enlarged to such an extent that surgery wouldn’t be an option. So, I was told I’d need to stay on blood thinners,” Davies recounted.
Until recently, Davies felt resigned to the “status quo.” He even sought another opinion, only to receive the same conclusion.
For AFib treatment, options usually include medications or a procedure known as “catheter ablation.” Dr. Paul Angaran, who directs cardiac arrhythmia at St. Michael’s Hospital in Toronto, described the process, saying, “Patients are generally sedated or fully asleep while we insert tubes into the groin and guide wires into the heart. We aim to target and destroy tissue around the pulmonary veins.”
This procedure involves making small scars in the heart that can help block the faulty signals causing irregular heartbeats, according to the Mayo Clinic. Dr. Gianluigi Bisleri, the director of minimally invasive and robotic cardiac surgery at the same hospital, explained, “We usually employ burning techniques to create these scars, although we might also use freezing methods. Either way, these scars become permanent, putting an end to the irregular heart rate.”
However, Angaran noted that such treatments might not be effective for everyone with AFib. In response, he partnered with Bisleri to craft a novel approach for patients.
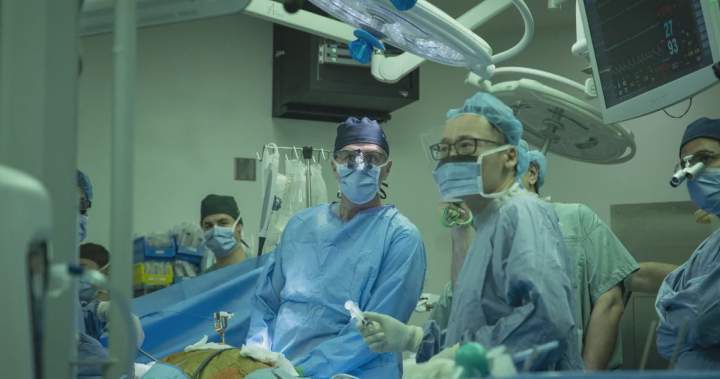
They developed a two-step robotic technique that combines external ablation with catheter techniques. “This not only allows us to leverage robotic technologies for better reach and vision of the heart but also enables us to treat larger areas,” Bisleri stated. This method represents a Canadian first, he added.
Patients wanting to undergo this procedure must be referred to Bisleri and Angaran. Still, Bisleri mentioned that while acquiring a referral is straightforward, awareness of their innovative approach is lacking.
There’s a waiting period of several weeks to months between each procedure, as Angaran pointed out that physicians prefer the external scars to heal before proceeding internally.
Davies was one of the first patients to try this new technique after learning about it through online research. He underwent the robotic part of the procedure in September and is set to return to Toronto soon for the catheter ablation phase.
“It’s encouraging to think that this diagnosis might lead to a more human-centric approach to treatment, which I genuinely appreciate compared to the alternatives,” he remarked.
Angaran noted that for patients with long-term persistent AFib, this method could yield a long-term success rate between 70 to 80 percent.





